
RESEARCH LIBRARY • PRODUCT-SPECIFIC GUIDE
CagriSema Research Overview
A comprehensive reference to combined amylin and GLP-1 receptor agonism, research observations, paired titration, and the Better Living Protocol.
CagriSema is the combination of Cagrilintide and Semaglutide, researched together for weight loss and metabolic health. Each works a different fullness system: Cagrilintide is a long-acting copy of amylin, the satiety hormone the pancreas releases alongside insulin, and Semaglutide is a long-acting copy of GLP-1, the gut hormone that signals a meal has landed. Hitting both at once produced larger weight loss in trials than either compound alone.
How CagriSema works
CagriSema engages two separate, complementary satiety systems rather than one:
- Cagrilintide acts on amylin and calcitonin receptors in the brainstem and hypothalamus, the regions that register fullness, to reduce food intake and meal size.
- Semaglutide acts on GLP-1 receptors in the brain’s appetite centers to reduce hunger, food noise, and cravings.
- Both slow how fast the stomach empties, so fullness lasts longer after a meal.
- Semaglutide increases insulin release only when blood sugar is elevated, while Cagrilintide blunts the post-meal rise in glucagon, together improving glucose handling.
- Because the two act on different receptors, their effects add together rather than overlap.
Typical real-world outcomes when used correctly
- Average body-weight reduction of 22.7% over 68 weeks in the Phase 3 REDEFINE-1 trial, versus 16.1% for Semaglutide alone and 11.8% for Cagrilintide alone.
- Average body-weight reduction of 13.7% over 68 weeks in adults with type 2 diabetes in REDEFINE-2, where weight loss is typically harder to achieve.
- Strong, lasting fullness after meals, with noticeably quieter food noise and fewer cravings.
- Better glucose control, HbA1c, and cardiometabolic markers.
- Stronger long-term results when combined with resistance training, high protein intake, hydration, and lifestyle changes.
Side effects and risks
- Gastrointestinal effects were the most common in trials, as with GLP-1 compounds: nausea, vomiting, diarrhea, constipation, reflux, or burping, mostly mild to moderate and concentrated during dose escalation.
- Other common effects include decreased appetite, fatigue or lower energy, headaches or dizziness, and injection-site redness, irritation, or discomfort.
- Less frequent or serious class risks include gallbladder issues, pancreatitis, and dehydration-related kidney stress tied to vomiting, diarrhea, or poor fluid intake.
- The combination is investigational and not FDA-approved. Semaglutide’s clinical formulations carry an FDA boxed warning for thyroid C-cell tumors, based on rodent studies; whether this applies to humans is unknown. The labels say not to use them with a personal or family history of medullary thyroid carcinoma (MTC) or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2).
- Seek medical care for severe side effects or medical issues and explain that GLP-1RA and amylin-analog peptides are involved.
What you may realistically observe over time
Why titration matters
The number-one reason people get mediocre results or quit early is rushing the dose and suffering unnecessary side effects. Slow, steady titration is the difference between “this is easy” and “I feel sick and stopped.”
- Gives the gastrointestinal system and brain time to adapt.
- Minimizes nausea, vomiting, reflux, and fatigue.
- Allows you to find a personal “sweet spot”: the lowest dose that delivers 85–95% of the maximum appetite-suppression and weight-loss effect.
Golden rules for titration
- Hold each levelStay on each dose for a minimum of four weeks before increasing.
- Increase only when neededOnly increase if appetite, cravings, or food noise are returning and side effects are minimal.
- Respond to side effectsIf nausea, reflux, constipation, or fatigue becomes significant, hold the current dose longer instead of increasing.
- Step back when necessaryIf side effects are too strong, consider returning to the previous tolerated level and reassessing.
- Aim for the lowest effective doseThe goal is not the highest dose. It is the lowest dose that produces consistent appetite control and sustainable progress.
How to know when you’ve found your dose
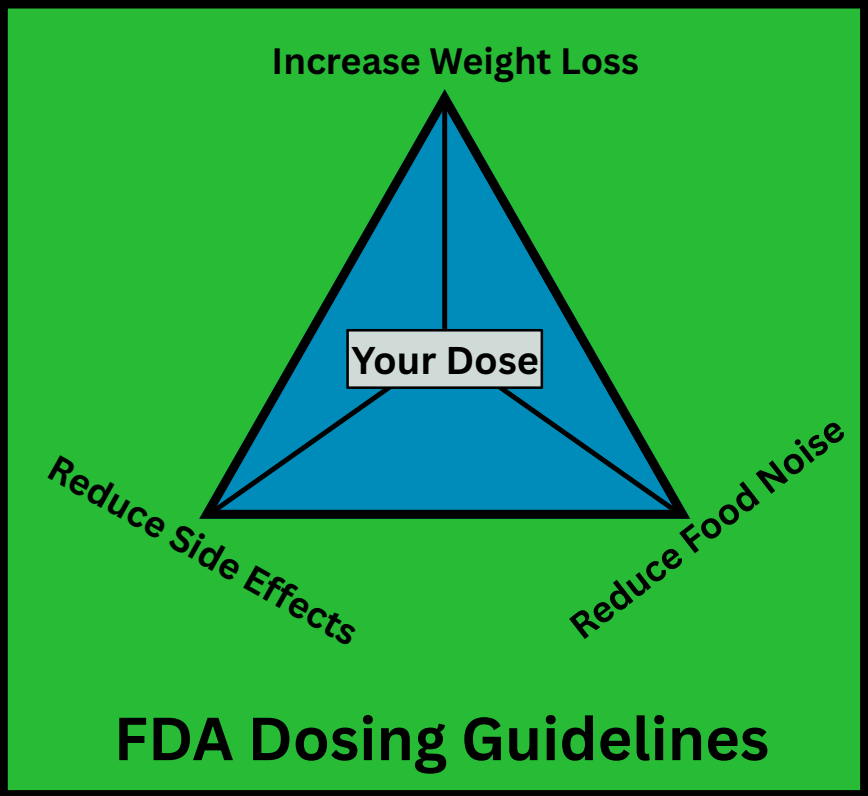
Dosing is a three-way balance: enough to keep weight coming off and food noise quiet, but not so much that side effects take over. The scale moves fastest when the peptide is combined with the lifestyle protocols below. Dose increases alone will not outrun a bad diet.
Phase 3 trial dosing for CagriSema
The REDEFINE trials escalated both compounds together, in equal doses, to 2.4mg of each once weekly (4.8mg combined). The combination is not FDA-approved; final guidelines are to be determined.
| Week | Cagrilintide | Semaglutide | Notes |
|---|---|---|---|
| 1–4 | 0.25mg5 units* | 0.25mg5 units* | Starting level; mainly used to assess tolerance. |
| 5–8 | 0.5mg10 units* | 0.5mg10 units* | First active escalation step; monitor tolerance. |
| 9–12 | 1mg20 units* | 1mg20 units* | Intermediate step; optional hold if side effects emerge. |
| 13–16 | 1.7mg34 units* | 1.7mg34 units* | Further escalation; only if tolerating well. |
| 17+ | 2.4mg48 units* | 2.4mg48 units* | Maximum target dose in trials; maintenance for evaluating long-term weight loss. |
*Unit figures assume both vials are reconstituted at 5mg per 1mL: 2mL of bacteriostatic water in each 10mg vial, so the unit count is the same for both compounds. On a standard 100-unit (1mL) insulin syringe, 1 unit = 0.05mg. Measure each compound from its own vial. In trials the two were given together as one weekly injection. If you use a different amount of water in either vial, recalculate that compound before drawing.
How to be wildly successful
This is not simply “take the peptide and eat whatever.” The people who get life-changing results treat the peptide like a powerful coach that removes excuses, then do the work.
- Record your baseline
- Take a before picture in good lighting with the least amount of clothing you are comfortable with.
- Weigh yourself in the morning on an empty stomach after using the bathroom.
- Weigh weekly in the same manner and at the same time of day.
- Track waist measurements, progress photos, and body composition if possible.
- Weight is useful, but waistline, photos, and strength are often better indicators when recomposition is happening.
- Know your numbers
- Calculate maintenance calories using BMR × activity factor or a reliable TDEE calculator.
- Create a moderate, sustainable calorie deficit.
- Avoid crash dieting; an overly aggressive deficit can worsen fatigue, muscle loss, cravings, and rebound eating.
- A consistent 500–1,000 calorie daily deficit is a common target for steady fat loss.
- Do not go extremely low calorie unless medically supervised.
- Use macros that protect muscle and keep you full
- Protein: aim for 0.8–1.2 grams per pound of body weight, or goal weight if significantly overweight.
- Example: a 180-pound person may target roughly 145–215 grams of protein per day.
- Use lean meats, eggs, Greek yogurt, cottage cheese, fish, protein shakes, or a high-quality whey isolate when whole food falls short.
- Prioritize carbohydrates around workouts and daily activity.
- Keep healthy fats in the plan while remembering they are calorie dense.
- Add fruits, vegetables, beans, oats, and other fiber sources to support digestion and fullness.
- Use meal planning to create freedom
- Plan meals ahead so low appetite does not lead to random under-eating or poor food choices.
- Keep three to five go-to high-protein meals you enjoy and prep simple options every few days.
- Do not rely on appetite alone to guide nutrition. Strong appetite suppression may require intentionally hitting protein, water, and electrolyte goals.
- Never walk into the kitchen hungry without a plan; that is when old habits can return.
- Build or preserve muscle
- Resistance training is non-negotiable for the best body-composition outcome.
- Lift weights three to four days per week; two days at minimum can still help greatly.
- Use challenging weight for 8–15 repetitions and aim for three to four hard sets per muscle group per week at minimum.
- Get close to failure while maintaining good form and progress by adding repetitions, weight, or better control.
- Walking 8,000–12,000 steps daily helps accelerate fat loss and improve health markers.
- Prioritize hydration and electrolytes
- Drink plenty of water throughout the day.
- Add electrolytes if headaches, fatigue, dizziness, or cramps appear.
- Keep sodium, potassium, and magnesium intake consistent.
- Avoid letting nausea or low appetite cause under-drinking.
- Protect sleep and manage stress
- Aim for seven to nine hours of quality sleep each night.
- Poor sleep increases hunger hormones and cravings, even when appetite is reduced.
- High stress can increase snacking, emotional eating, and poor food choices.
- Keep a simple nighttime routine and protect sleep as part of the protocol.
- Make the mindset shiftThis is not a 12-week cut. The peptide is a 6–24-month bridge for installing habits that last. Whether or not you later stop the peptide, the habits you build are what help keep weight off.
Simple electrolyte option from the source guide
• ¼–½ teaspoon salt
• ½ teaspoon potassium citrate
• ¼ teaspoon baking soda
• Lemon, sweetener, or low-calorie drink mix
Quick-reference checklist
- Hit your protein goal every day.
- Maintain a consistent calorie deficit.
- Lift weights three to four times per week, with two as the minimum.
- Walk 8,000–12,000 steps daily.
- Drink water and use electrolytes as needed.
- Get seven to nine hours of sleep.
- Plan meals before hunger hits.
- Track weekly progress photos and measurements.
- Increase dose only when needed and well tolerated.
- Focus on habits, not just the scale.
Related research
Explore CagriSema
CagriSema is two compounds used together. View both research materials available at BLP Research.
Research use only
This reference is provided for laboratory and research purposes only. All materials are sold and offered strictly for research use and are not intended to diagnose, treat, cure, or prevent any disease. Statements have not been evaluated by the Food and Drug Administration.